

Volume 13, Issue 2 (Spring 2026)
JROS 2026, 13(2): 57-64 |
Back to browse issues page




Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Chehrassan M, Nikouei F, Shakeri M, Kiaei S M S, Falakeh S, Ghavidel E, et al . Is Surgery Justified for Adolescent Idiopathic Scoliosis Between 35° and 45°?. JROS 2026; 13 (2) :57-64
URL: http://jros.iums.ac.ir/article-1-2319-en.html
URL: http://jros.iums.ac.ir/article-1-2319-en.html
Mohammadreza Chehrassan1 

 , Farshad Nikouei1 , Mohammadreza Shakeri1 , Seyed Matin Sadat Kiaei1 , Saba Falakeh1 , Ehsan Ghavidel1 , Ebrahim Ameri Mahabadi1 , Hasan Ghandhari1
1- Department of Orthopedics, Bone and Joint Reconstruction Research Center, School of Medicine, Iran University of Medical Sciences, Tehran, Iran.
Keywords: Adolescent idiopathic scoliosis (AIS), Posterior spinal fusion (PSF), Scoliosis surgery, Scoliosis Research Society-22r (SRS-22r) questionnaire, Patient-reported outcome measures, Self-image
Full-Text [PDF 2473 kb]
(84 Downloads)
| Abstract (HTML) (650 Views)
Full-Text: (35 Views)
Introduction
Adolescent idiopathic scoliosis (AIS) is the most common type of scoliosis, with treatment options ranging from observation or bracing to surgery [1, 2]. Surgery is typically reserved for patients with severe curves, especially those with Cobb angles >40–45°, due to the risk of curve progression and potential complications [3, 4]. However, this threshold may overlook patients who could benefit from surgery.
In addition to Cobb angle, factors, such as coronal imbalance, curve progression despite conservative management, and significant back pain influence surgical decisions, even for mild-to-moderate curves [5, 6]. Despite this, there is limited evidence on surgical outcomes for AIS patients with curves between 35° and 45°, a group often considered for conservative management. Most studies on AIS treatments focus on surgical approaches for advanced deformities, overlooking patients with intermediate curvatures but significant clinical symptoms [7-12].
This study aimed to evaluate the role of corrective posterior spinal fusion (PSF) surgery in AIS patients with Cobb angles between 35° and 45° to focus on radiologic and clinical outcomes.
Methods
This retrospective cohort study was conducted at two tertiary orthopedic hospitals. Ethical approval for this study was obtained from the institutional review board. Data were collected from patients aged 10-20 years who underwent PSF surgery for AIS between March 2021 and April 2024. Eligible patients demonstrated a preoperative main Cobb angle between 35° and 45°, measured on standing total-spine anteroposterior radiographs. All Lenke curve types were included to represent the full spectrum of AIS curve patterns. The follow-up period was at least one year. Patients were excluded if they had incomplete clinical or radiographic data, a history of previous spinal surgery, or any other spinal pathology that could influence surgical outcomes.
Demographic and clinical data were extracted from medical records, including age at surgery, sex, history of bracing, and follow-up duration. Radiographic parameters were assessed preoperatively and at the last follow-up.
Radiographic evaluation included measurements of the main Cobb angle, thoracic kyphosis (TK), lumbar lordosis (LL), sacral slope, pelvic tilt (PT), pelvic obliquity, radiographic shoulder height, coronal balance, and sagittal balance. All measurements were performed on standing full-spine anteroposterior and lateral radiographs by two spine surgeons.
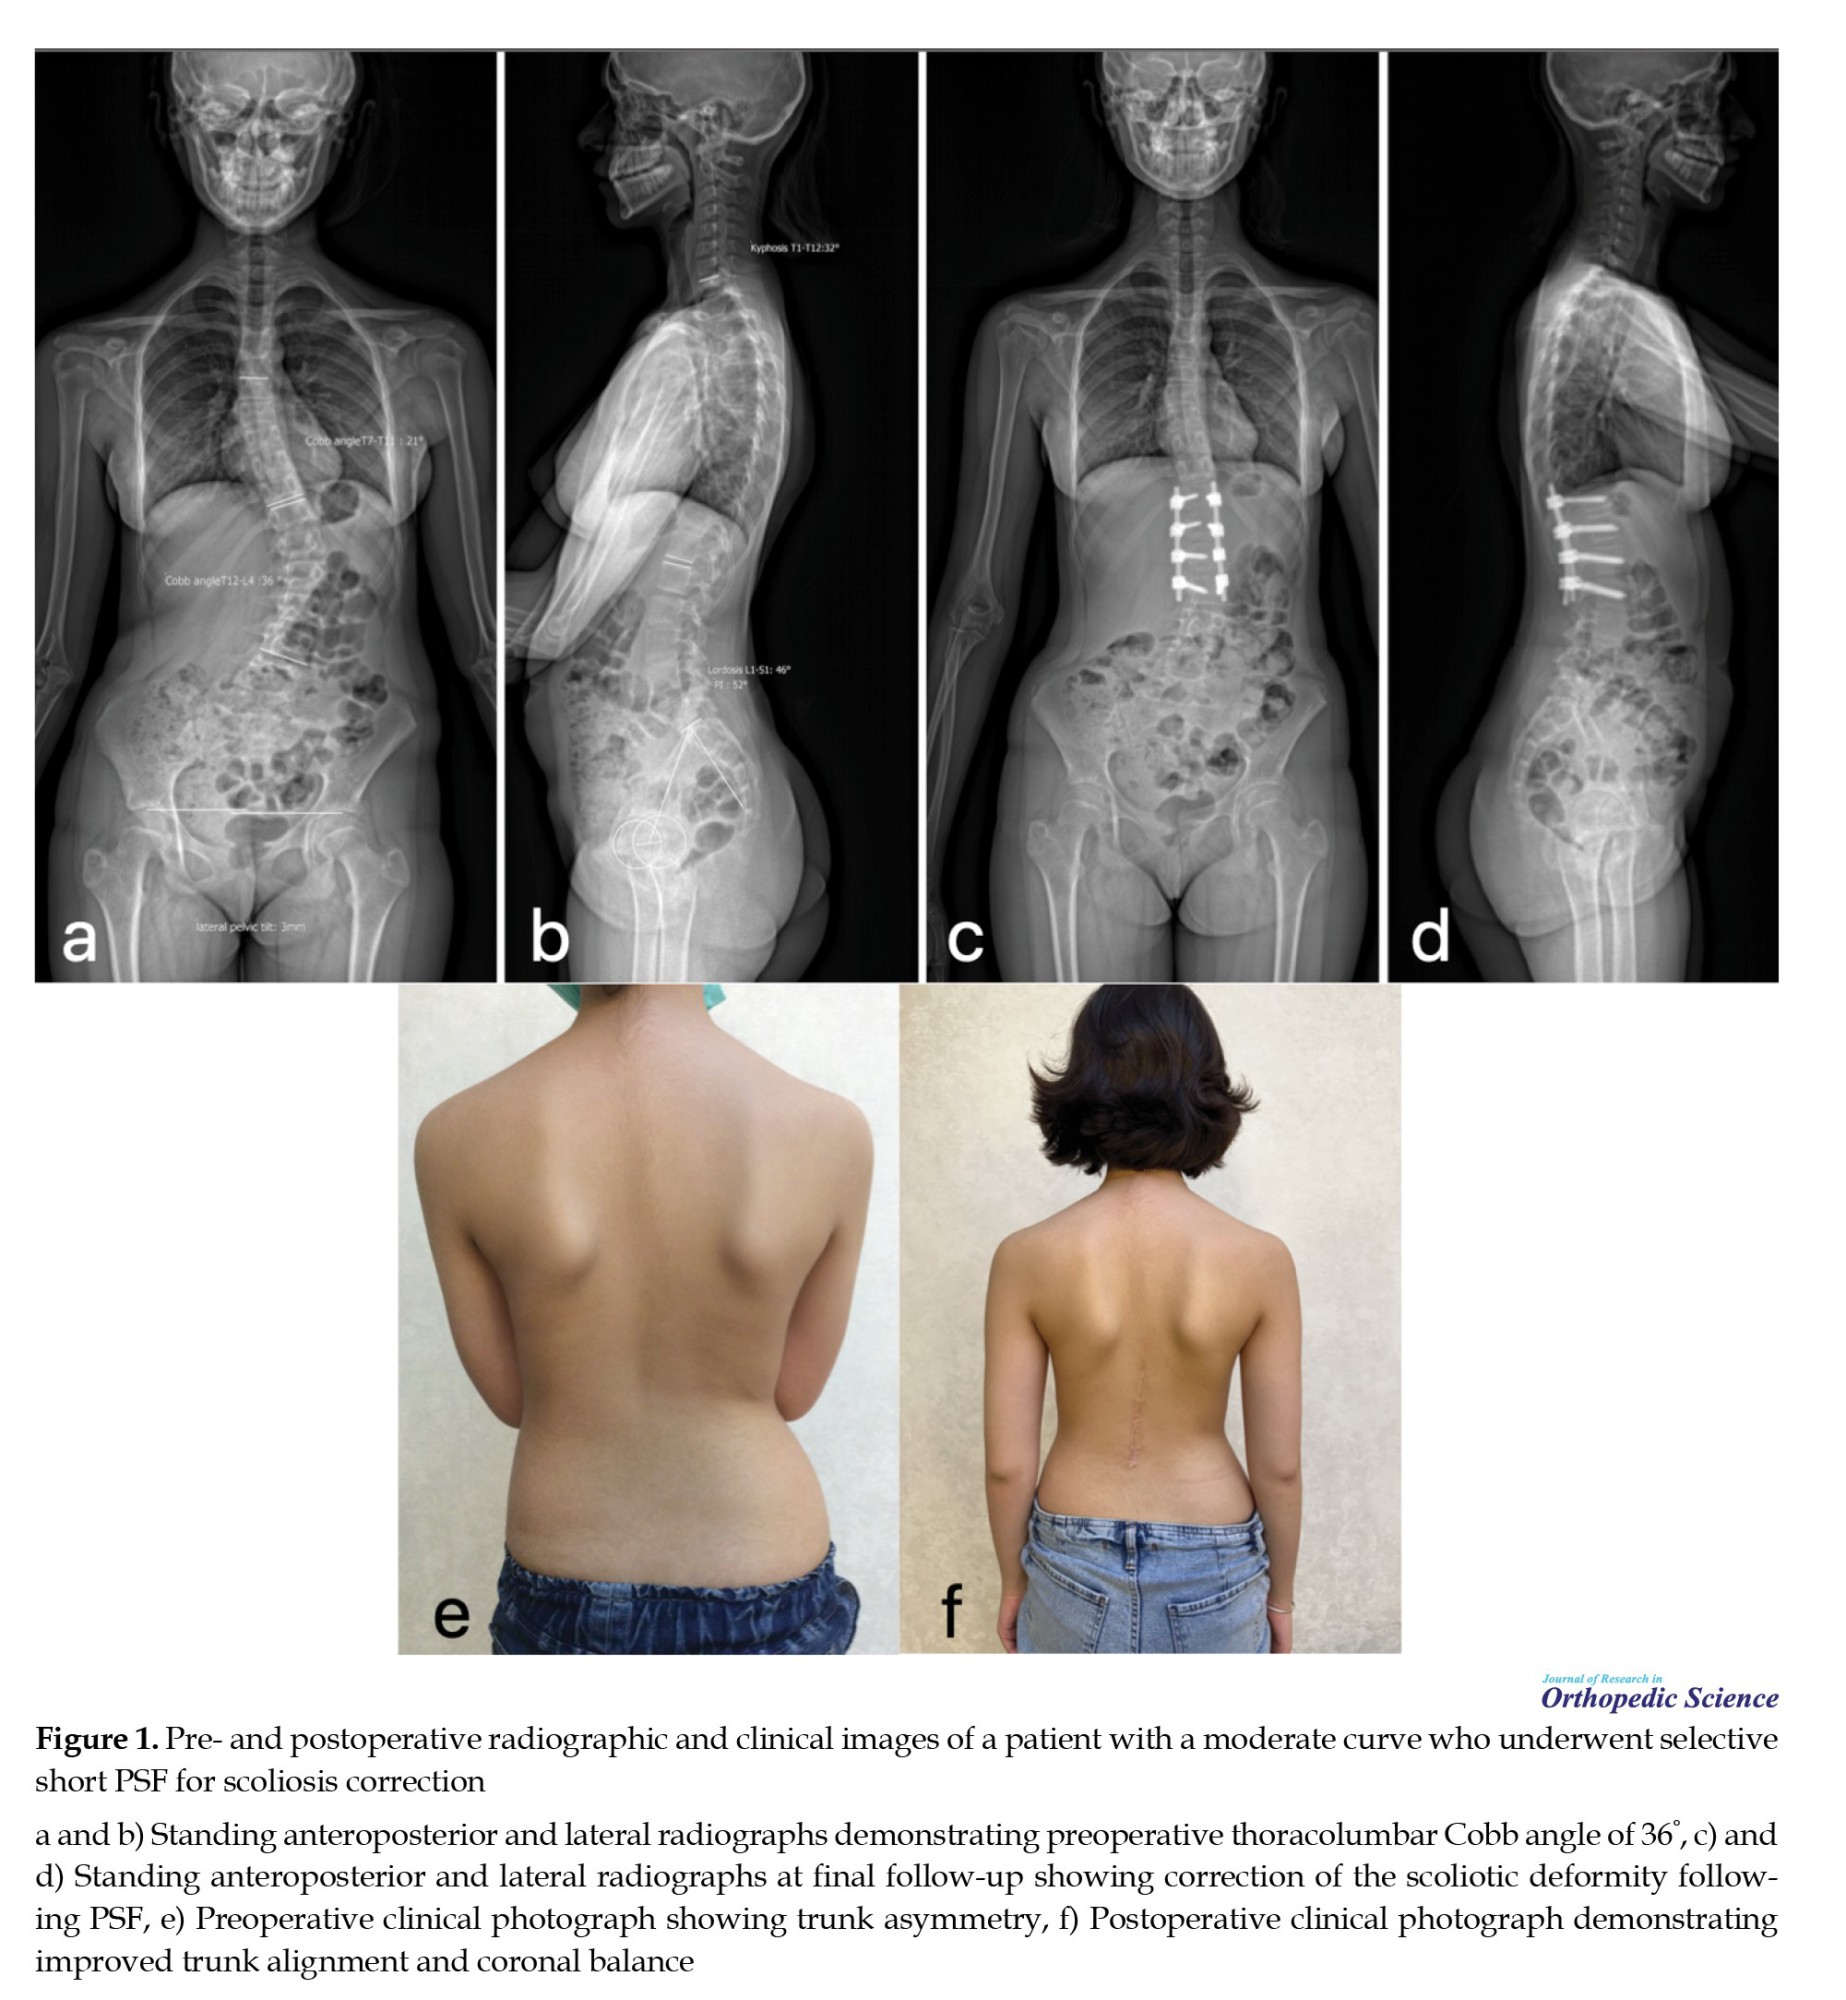
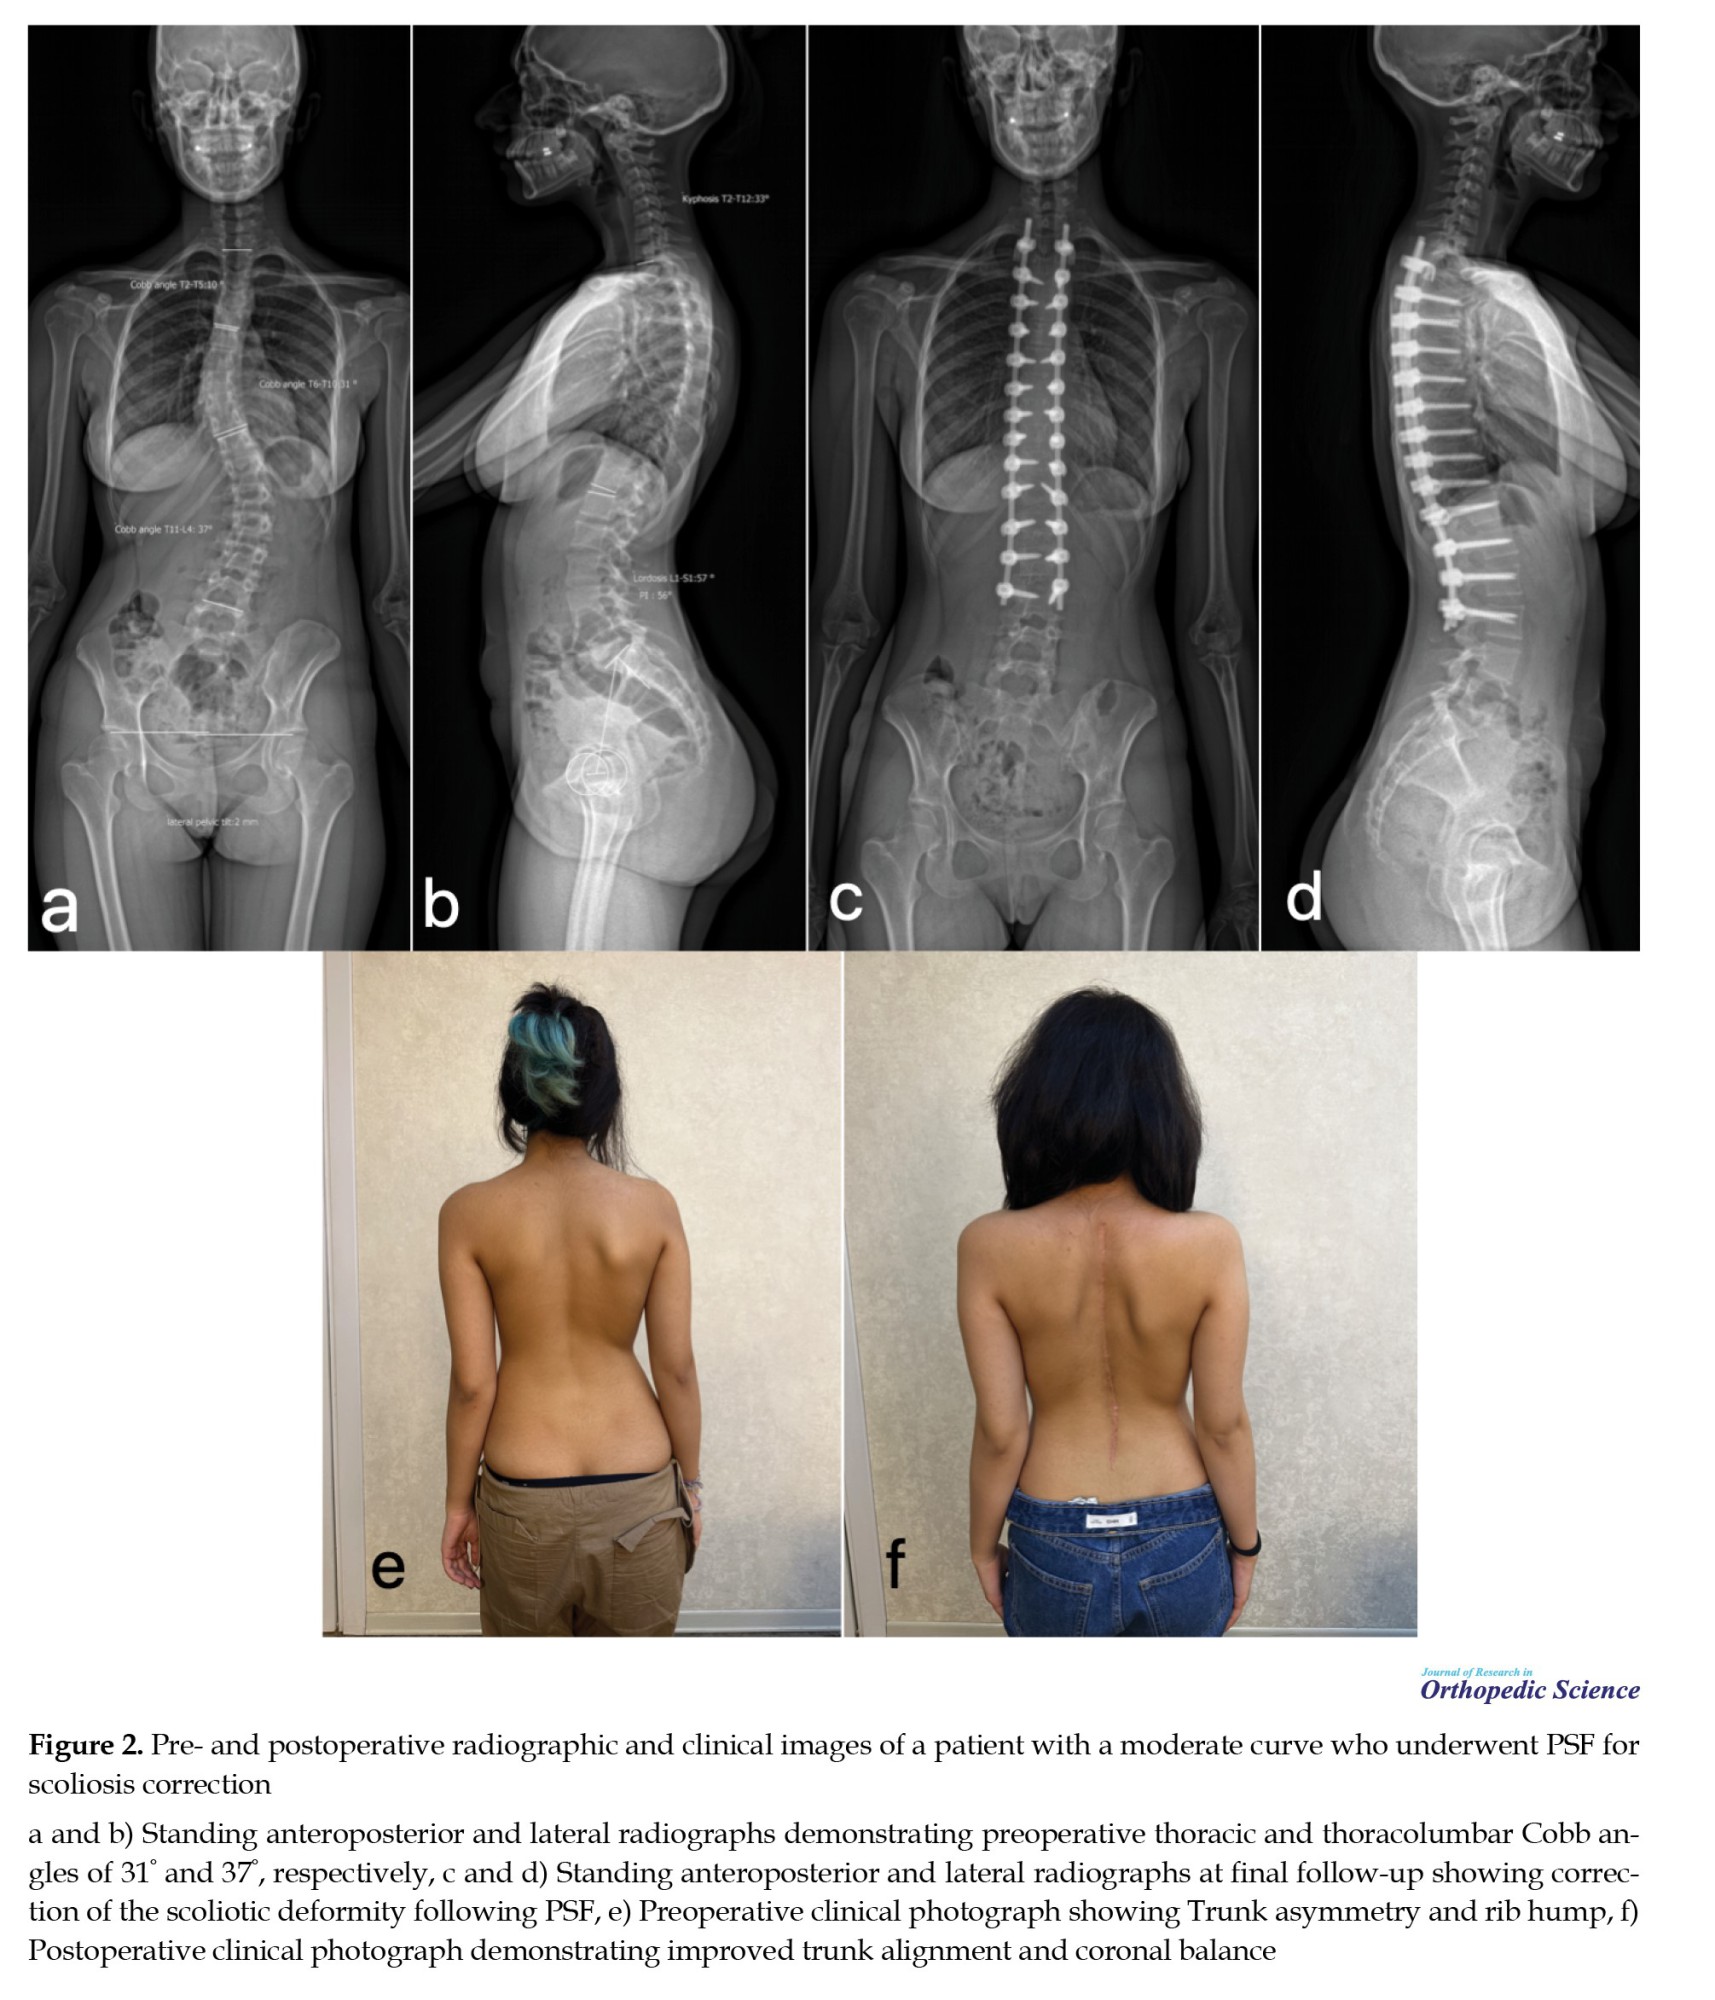
Surgical data collected included the levels of upper and lower instrumented vertebrae and classification of the surgery as selective or non-selective. Surgeries were considered selective if instrumentation included only the main structural curve (Figures 1 and 2).
 Health-related quality of life was assessed using the scoliosis research society-22r (SRS-22r) questionnaire, which consists of 22 items divided into five domains: Self-image/appearance, function/activity, pain, mental health, and satisfaction with management. Higher scores indicate a better quality of life. The questionnaire was administered preoperatively and at last follow-up to evaluate changes in patient-reported outcomes. A validated Persian version of the SRS-22r was used [13, 14].
Statistical analysis was performed using SPSS software, version 19. Continuous variables were reported as Mean±SD, and categorical variables as frequencies and percentages. The normality of data was assessed using the Kolmogorov-Smirnov test, and paired t-tests were used to compare preoperative and last follow-up radiographic parameters and SRS-22r scores. A P<0.05 was considered statistically significant.
Results
A total of 40 patients with AIS and preoperative Cobb angles <45° were included. The cohort consisted of 36 females (90%) and 4 males (10%), with a mean age of 15.58±2.76 years at surgery. The mean follow-up duration was 20.84±12.69 months. Eighteen patients (45%) had a history of brace treatment, while 55% did not. The most common Lenke classification was type 5 (55%), followed by type 1 (22.5%), type 6 (15%), type 3 (5%), and type 2 (2.5%) (Table 1).

Significant improvements were observed in scoliotic curves after surgery. The mean preoperative thoracic Cobb angle decreased from 31.35±9.84° to 10.96±7.07° (P<0.001), and the thoracolumbar Cobb angle reduced from 34.03±9.08° to 11.60±7.48° (P<0.001). Postoperative TK decreased significantly from 43.92±13.86° to 37.38±12.09° (P=0.027), and LL decreased from 58.97±11.97° to 51.20±11.69° (P=0.002). PT showed a slight but significant increase (P=0.043), while changes in sacral slope did not reach statistical significance (P=0.058). Additionally, no significant changes were observed in coronal and sagittal balance, shoulder height, or pelvic obliquity following surgery. Table 2 presents the complete preoperative and postoperative radiologic measurements.

The mean total SRS-22r score improved significantly from 3.59±0.65 preoperatively to 3.98±0.54 postoperatively (P<0.001). Among the individual domains, self-image improved significantly (P=0.008), and satisfaction with management increased markedly from 2.63±1.29 to 4.30±0.72 (P<0.001). Although the pain and function subdomains demonstrated improvements, only the change in function approached statistical significance (P=0.001), while changes in mental health were not statistically significant (P=0.486). Table 3 presents the detailed preoperative and postoperative SRS-22r scores.

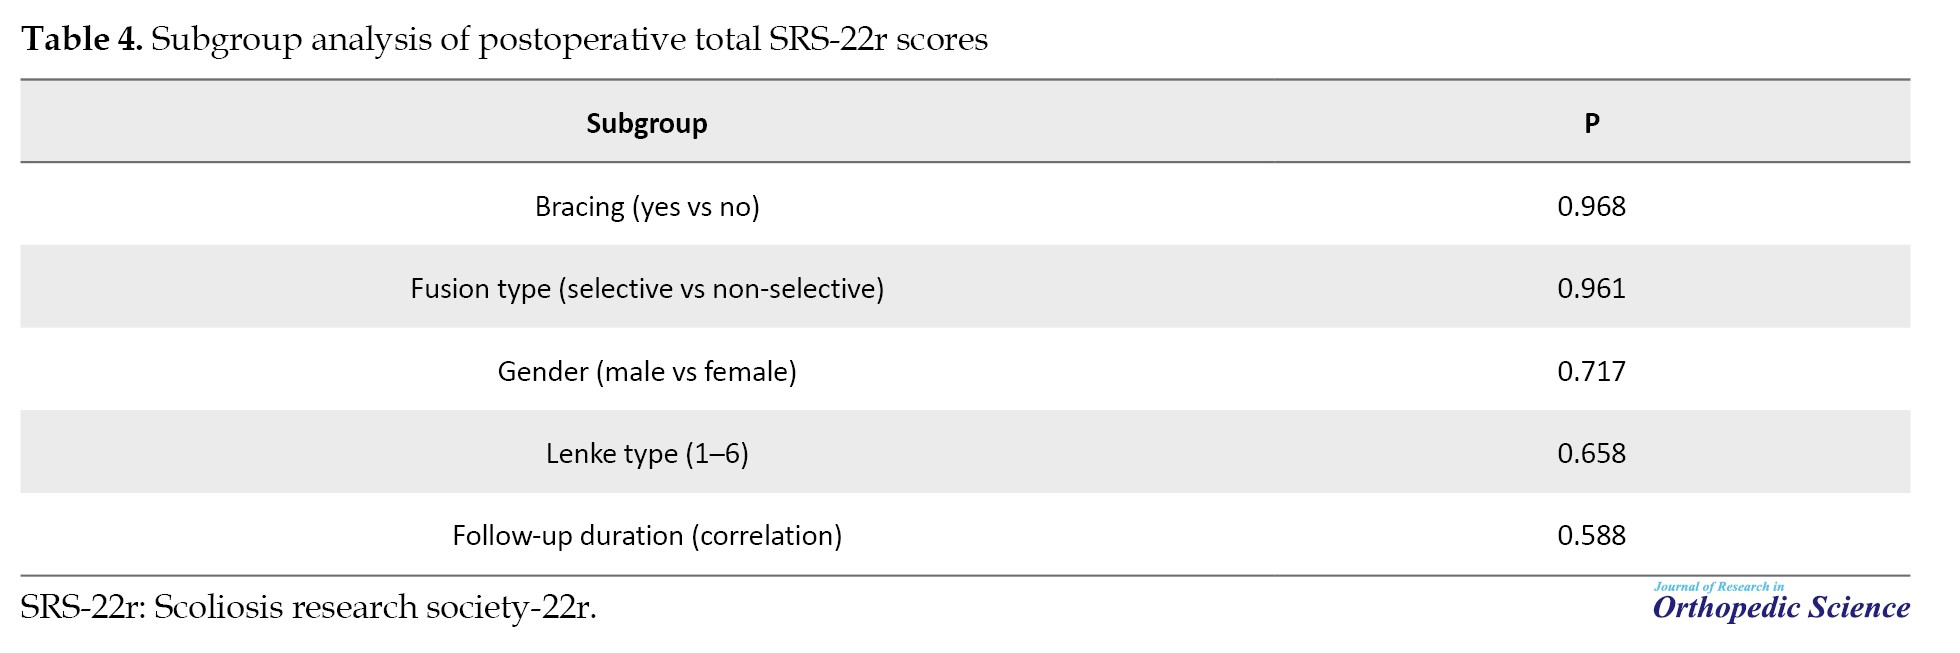
Further analysis revealed no statistically significant differences in postoperative SRS scores based on prior bracing, selective versus non-selective fusion, gender, or Lenke classification. Additionally, no correlation was found between follow-up duration and clinical outcomes. Table 4 presents detailed results of these analyses.
Discussion
Our findings are consistent with those of previous studies that have shown significant improvements in total PROMs, particularly in the self-image and satisfaction with management domains, following surgical correction for AIS. Several studies have demonstrated meaningful postoperative gains in these areas [8-10]. In addition, studies using minimal clinically important difference (MCID) thresholds have further validated self-image and satisfaction as the most responsive and meaningful domains after surgery [10, 11]. Fernandes et al. reported that 96.4% of patients reached MCID in self-image, while domains including pain and function often failed to meet clinical relevance [12]. A key difference is that these studies either excluded or did not isolate patients with moderate curves (35–45°), a population frequently caught in the gray zone of surgical decision-making. By specifically evaluating this underrepresented group, our study confirm that such patients can also experience substantial subjective improvement despite having less severe deformities.
Our results also consistent with the findings of previous studies emphasized that improvements in PROMs—particularly self-image and satisfaction with management—often occur independent of the degree of curve correction, deformity magnitude, or instrumentation type [10, 13, 14]. In our cohort, although the Cobb angle was significantly corrected, other radiologic parameters such as spinopelvic parameters and sagittal and coronal balance did not change substantially. Yet, patients still reported meaningful improvement in self-image and satisfaction with management. This supports the notion that radiologic changes alone may not fully explain the benefits of surgery, and that PROMs can reflect a broader psychosocial response. However, it should be noted that this relationship remains controversial, as other studies, such as Chaudhary et al.’s study, reported a strong correlation between Cobb correction and PROM gains [15].
In a longitudinal study by Diarbakerli et al., non-operative and brace-treated patients showed slightly better health-related quality of life than those who had undergone surgery [16]. However, it is important to note that patients who undergo surgery often present with more severe curves and greater spinal imbalance, which can inherently influence their outcomes. Diarbakerli’s findings suggest that quality of life tends to equilibrate across treatment groups over time. Our study, by focusing on early postoperative results in a moderate curve population, provides valuable context for short-term decision-making. It highlights that even patients with mid-range deformities can achieve significant gains in self-image, satisfaction with management, and function, which are especially relevant during adolescence—a period when psychosocial concerns reach a peak.
Conclusion
This study highlights that patients with AIS and moderate curves (35–45°) can experience significant improvements in self-image, satisfaction with management, and function following surgical correction, even with limited radiologic changes beyond Cobb angle correction. These findings emphasize the importance of incorporating patient-reported outcomes into surgical decision-making, especially for patients in the gray zone between operative and conservative treatments.
Limitations and future research
This study has several limitations that should be acknowledged. First, the sample size was relatively small, which may limit the generalizability of our findings. Larger, multicenter studies would help validate these results and provide broader applicability. Second, the follow-up period was limited to early postoperative outcomes. While our findings offer important insight into the short-term benefits of surgery in AIS patients with moderate curves, longer follow-up is necessary to determine the durability of these improvements as patients transition into adulthood. Furthermore, while we observed significant improvements in PROMs, particularly in self-image and satisfaction, we acknowledge that these subjective measures may be influenced by individual expectations, cultural factors, and psychosocial context—elements that were not fully captured in our analysis. Lastly, the lack of a non-operative comparison group limits our ability to directly compare surgical outcomes with those of conservative management in moderate AIS cases. Including a matched non-operative cohort in future studies would help clarify the relative benefits of surgical intervention in this “gray zone” population and inform more personalized, evidence-based treatment decisions.
Ethical Considerations
Compliance with ethical guidelines
All procedures performed in studies involving human participants were in accordance with the ethical standards of the institutional and/or national research committee and the 1964 Declaration of Helsinki and its later amendments or comparable ethical standards. This study was approved by the Ethics Committee of the Iran University of Medical Sciences, Tehran, Iran (Code: IR.IUMS.REC.1403.284).
Funding
This research did not receive any grant from funding agencies in the public, commercial, or non-profit sectors.
Authors' contributions
Conceptualization, study design, and data analysis: Saba Falakeh and Mohammadreza Chehrassan; Data collection: Saba Falakeh, Mohammadreza Chehrassan, and Ehsan Ghavidel; Data analysis: Seyed Matin Sadat Kiaei; Investigation: Hasan Ghandhari; Writing: Seyed Matin Sadat Kiaei, Mohammadreza Shakeri and Farshad Nikouei; Final approval: Ebrahim Ameri Mahabadi.
Conflict of interest
The authors declared no conflict of interest.
References
Adolescent idiopathic scoliosis (AIS) is the most common type of scoliosis, with treatment options ranging from observation or bracing to surgery [1, 2]. Surgery is typically reserved for patients with severe curves, especially those with Cobb angles >40–45°, due to the risk of curve progression and potential complications [3, 4]. However, this threshold may overlook patients who could benefit from surgery.
In addition to Cobb angle, factors, such as coronal imbalance, curve progression despite conservative management, and significant back pain influence surgical decisions, even for mild-to-moderate curves [5, 6]. Despite this, there is limited evidence on surgical outcomes for AIS patients with curves between 35° and 45°, a group often considered for conservative management. Most studies on AIS treatments focus on surgical approaches for advanced deformities, overlooking patients with intermediate curvatures but significant clinical symptoms [7-12].
This study aimed to evaluate the role of corrective posterior spinal fusion (PSF) surgery in AIS patients with Cobb angles between 35° and 45° to focus on radiologic and clinical outcomes.
Methods
This retrospective cohort study was conducted at two tertiary orthopedic hospitals. Ethical approval for this study was obtained from the institutional review board. Data were collected from patients aged 10-20 years who underwent PSF surgery for AIS between March 2021 and April 2024. Eligible patients demonstrated a preoperative main Cobb angle between 35° and 45°, measured on standing total-spine anteroposterior radiographs. All Lenke curve types were included to represent the full spectrum of AIS curve patterns. The follow-up period was at least one year. Patients were excluded if they had incomplete clinical or radiographic data, a history of previous spinal surgery, or any other spinal pathology that could influence surgical outcomes.
Demographic and clinical data were extracted from medical records, including age at surgery, sex, history of bracing, and follow-up duration. Radiographic parameters were assessed preoperatively and at the last follow-up.
Radiographic evaluation included measurements of the main Cobb angle, thoracic kyphosis (TK), lumbar lordosis (LL), sacral slope, pelvic tilt (PT), pelvic obliquity, radiographic shoulder height, coronal balance, and sagittal balance. All measurements were performed on standing full-spine anteroposterior and lateral radiographs by two spine surgeons.
Surgical data collected included the levels of upper and lower instrumented vertebrae and classification of the surgery as selective or non-selective. Surgeries were considered selective if instrumentation included only the main structural curve (Figures 1 and 2).
Statistical analysis was performed using SPSS software, version 19. Continuous variables were reported as Mean±SD, and categorical variables as frequencies and percentages. The normality of data was assessed using the Kolmogorov-Smirnov test, and paired t-tests were used to compare preoperative and last follow-up radiographic parameters and SRS-22r scores. A P<0.05 was considered statistically significant.
Results
A total of 40 patients with AIS and preoperative Cobb angles <45° were included. The cohort consisted of 36 females (90%) and 4 males (10%), with a mean age of 15.58±2.76 years at surgery. The mean follow-up duration was 20.84±12.69 months. Eighteen patients (45%) had a history of brace treatment, while 55% did not. The most common Lenke classification was type 5 (55%), followed by type 1 (22.5%), type 6 (15%), type 3 (5%), and type 2 (2.5%) (Table 1).
Significant improvements were observed in scoliotic curves after surgery. The mean preoperative thoracic Cobb angle decreased from 31.35±9.84° to 10.96±7.07° (P<0.001), and the thoracolumbar Cobb angle reduced from 34.03±9.08° to 11.60±7.48° (P<0.001). Postoperative TK decreased significantly from 43.92±13.86° to 37.38±12.09° (P=0.027), and LL decreased from 58.97±11.97° to 51.20±11.69° (P=0.002). PT showed a slight but significant increase (P=0.043), while changes in sacral slope did not reach statistical significance (P=0.058). Additionally, no significant changes were observed in coronal and sagittal balance, shoulder height, or pelvic obliquity following surgery. Table 2 presents the complete preoperative and postoperative radiologic measurements.
The mean total SRS-22r score improved significantly from 3.59±0.65 preoperatively to 3.98±0.54 postoperatively (P<0.001). Among the individual domains, self-image improved significantly (P=0.008), and satisfaction with management increased markedly from 2.63±1.29 to 4.30±0.72 (P<0.001). Although the pain and function subdomains demonstrated improvements, only the change in function approached statistical significance (P=0.001), while changes in mental health were not statistically significant (P=0.486). Table 3 presents the detailed preoperative and postoperative SRS-22r scores.
Further analysis revealed no statistically significant differences in postoperative SRS scores based on prior bracing, selective versus non-selective fusion, gender, or Lenke classification. Additionally, no correlation was found between follow-up duration and clinical outcomes. Table 4 presents detailed results of these analyses.
Discussion
Our findings are consistent with those of previous studies that have shown significant improvements in total PROMs, particularly in the self-image and satisfaction with management domains, following surgical correction for AIS. Several studies have demonstrated meaningful postoperative gains in these areas [8-10]. In addition, studies using minimal clinically important difference (MCID) thresholds have further validated self-image and satisfaction as the most responsive and meaningful domains after surgery [10, 11]. Fernandes et al. reported that 96.4% of patients reached MCID in self-image, while domains including pain and function often failed to meet clinical relevance [12]. A key difference is that these studies either excluded or did not isolate patients with moderate curves (35–45°), a population frequently caught in the gray zone of surgical decision-making. By specifically evaluating this underrepresented group, our study confirm that such patients can also experience substantial subjective improvement despite having less severe deformities.
Our results also consistent with the findings of previous studies emphasized that improvements in PROMs—particularly self-image and satisfaction with management—often occur independent of the degree of curve correction, deformity magnitude, or instrumentation type [10, 13, 14]. In our cohort, although the Cobb angle was significantly corrected, other radiologic parameters such as spinopelvic parameters and sagittal and coronal balance did not change substantially. Yet, patients still reported meaningful improvement in self-image and satisfaction with management. This supports the notion that radiologic changes alone may not fully explain the benefits of surgery, and that PROMs can reflect a broader psychosocial response. However, it should be noted that this relationship remains controversial, as other studies, such as Chaudhary et al.’s study, reported a strong correlation between Cobb correction and PROM gains [15].
In a longitudinal study by Diarbakerli et al., non-operative and brace-treated patients showed slightly better health-related quality of life than those who had undergone surgery [16]. However, it is important to note that patients who undergo surgery often present with more severe curves and greater spinal imbalance, which can inherently influence their outcomes. Diarbakerli’s findings suggest that quality of life tends to equilibrate across treatment groups over time. Our study, by focusing on early postoperative results in a moderate curve population, provides valuable context for short-term decision-making. It highlights that even patients with mid-range deformities can achieve significant gains in self-image, satisfaction with management, and function, which are especially relevant during adolescence—a period when psychosocial concerns reach a peak.
Conclusion
This study highlights that patients with AIS and moderate curves (35–45°) can experience significant improvements in self-image, satisfaction with management, and function following surgical correction, even with limited radiologic changes beyond Cobb angle correction. These findings emphasize the importance of incorporating patient-reported outcomes into surgical decision-making, especially for patients in the gray zone between operative and conservative treatments.
Limitations and future research
This study has several limitations that should be acknowledged. First, the sample size was relatively small, which may limit the generalizability of our findings. Larger, multicenter studies would help validate these results and provide broader applicability. Second, the follow-up period was limited to early postoperative outcomes. While our findings offer important insight into the short-term benefits of surgery in AIS patients with moderate curves, longer follow-up is necessary to determine the durability of these improvements as patients transition into adulthood. Furthermore, while we observed significant improvements in PROMs, particularly in self-image and satisfaction, we acknowledge that these subjective measures may be influenced by individual expectations, cultural factors, and psychosocial context—elements that were not fully captured in our analysis. Lastly, the lack of a non-operative comparison group limits our ability to directly compare surgical outcomes with those of conservative management in moderate AIS cases. Including a matched non-operative cohort in future studies would help clarify the relative benefits of surgical intervention in this “gray zone” population and inform more personalized, evidence-based treatment decisions.
Ethical Considerations
Compliance with ethical guidelines
All procedures performed in studies involving human participants were in accordance with the ethical standards of the institutional and/or national research committee and the 1964 Declaration of Helsinki and its later amendments or comparable ethical standards. This study was approved by the Ethics Committee of the Iran University of Medical Sciences, Tehran, Iran (Code: IR.IUMS.REC.1403.284).
Funding
This research did not receive any grant from funding agencies in the public, commercial, or non-profit sectors.
Authors' contributions
Conceptualization, study design, and data analysis: Saba Falakeh and Mohammadreza Chehrassan; Data collection: Saba Falakeh, Mohammadreza Chehrassan, and Ehsan Ghavidel; Data analysis: Seyed Matin Sadat Kiaei; Investigation: Hasan Ghandhari; Writing: Seyed Matin Sadat Kiaei, Mohammadreza Shakeri and Farshad Nikouei; Final approval: Ebrahim Ameri Mahabadi.
Conflict of interest
The authors declared no conflict of interest.
References
- Weinstein SL, Dolan LA, Cheng JC, Danielsson A, Morcuende JA. Adolescent idiopathic scoliosis. Lancet. 2008; 371(9623):1527-37. [DOI:10.1016/s0140-6736(08)60658-3] [PMID]
- Altaf F, Gibson A, Dannawi Z, Noordeen H. Adolescent idiopathic scoliosis. BMJ. 2013; 346:f2508. [DOI:10.1136/bmj.f2508] [PMID]
- Scoliosis Research Society (SRS). Surgery for adolescent idiopathic scoliosis. Milwaukee: Scoliosis Research Society; 2026. [Link]
- Lonstein JE. Adolescent idiopathic scoliosis: Screening and diagnosis. Instr Course Lect. 1989; 38:105–13. [PMID]
- Karol LA. The natural history of adolescent idiopathic scoliosis. J Pediatr Orthop. 2011; 39(6):S38-43. [Link]
- Weinstein SL, Dolan LA, Wright JG, Dobbs MB. Effects of bracing in adolescents with idiopathic scoliosis. N Engl J Med. 2013; 369(16):1512-21. [DOI:10.1056/nejmoa1307337] [PMID]
- Bridwell KH. Surgical treatment of idiopathic adolescent scoliosis. Spine (Phila Pa 1976). 1999; 24(24):2607-16. [DOI:10.1097/00007632-199912150-00008] [PMID]
- Asher M, Min Lai S, Burton D, Manna B. The reliability and concurrent validity of the scoliosis research society-22 patient questionnaire for idiopathic scoliosis. Spine (Phila Pa 1976). 2003; 28(1):63-9. [DOI:10.1097/00007632-200301010-00015] [PMID]
- Carreon LY, Sanders JO, Diab M, Sturm PF, Sucato DJ; Spinal deformity study group. Patient satisfaction after surgical correction of adolescent idiopathic scoliosis. Spine (Phila Pa 1976). 2011; 36(12):965-8. [DOI:10.1097/brs.0b013e3181e92b1d] [PMID]
- Bagó J, Pérez-Grueso FJ, Les E, Hernández P, Pellisé F. Minimal important differences of the SRS-22 patient questionnaire following surgical treatment of idiopathic scoliosis. Eur Spine J. 2009; 18(12):1898-904. [DOI:10.1007/s00586-009-1066-x] [PMID]
- Çolak TK, Akgül T, Çolak I, Dereli EE, Chodza M, Dikici F. Health related quality of life and perception of deformity in patients with adolescent idiopathic scoliosis. J Back Musculoskelet Rehabil. 2017; 30(3):597-602. [DOI:10.3233/bmr-160564] [PMID]
- Berven S, Baron M, Deviren V, Glassman S, Bridwell K, Verma K. The assessment of clinically significant differences in treating spinal deformity using the SRs questionnaire: what is the threshold of change that is meaningful to patients? Int J Spine Surg. 2019 ;13(2):153-7. [DOI:10.14444/6020] [PMID]
- Westrick ER, Ward WT. Adolescent idiopathic scoliosis: 5-year to 20-year evidence-based surgical results. J Pediatr Orthop. 2011; 31(1 Suppl):S61-8. [DOI:10.1097/bpo.0b013e3181fd87d5] [PMID]
- Abel MF, Herndon SK, Sauer LD, Novicoff WM, Smith JS, Shaffrey CI, et al. Selective versus nonselective fusion for idiopathic scoliosis: does lumbosacral takeoff angle change? Spine (Phila Pa 1976). 2011; 36(14):1103-12. [DOI:10.1097/brs.0b013e3181f60b5b] [PMID]
- Chaudhary RK, Kaucha D, Banskota B, Barakoti RK, Banskota AK. Correlation between radiological outcome and health related quality of life after posterior spinal fusion for adolescent idiopathic scoliosis. J Nepal Health Res Counc. 2021; 19(1):44-7. [DOI:10.33314/jnhrc.v19i1.3245] [PMID]
- Danielsson AJ, Wiklund I, Pehrsson K, Nachemson AL. Health-related quality of life in patients with adolescent idiopathic scoliosis: A matched follow-up at least 20 years after treatment with brace or surgery. Eur Spine J. 2001; 10(4):278-88. [DOI:10.1007/s005860100309]
Type of Study: Research Article |
Subject:
Spine surgery
Received: 2025/08/3 | Accepted: 2026/02/4 | Published: 2026/04/1
Received: 2025/08/3 | Accepted: 2026/02/4 | Published: 2026/04/1
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

Copyright © The Author(s);
This is an open access article distributed under the terms of the Creative Commons Attribution License (CC-By-NC), which permits use, distribution, and reproduction in any medium, provided the original work is properly cited and is not used for commercial purposes.
Contact Information
